
- For reversal of post-operative respiratory depression and coma: 20-40mcg IV PRN
- For opioid overdose: 40-400 mcg IV PRN
- Infusion: If an infusion is required, commence the infusion with an hourly infusion rate calculated as 2/3rd of the total bolus dose given to achieve the desired opioid reversal effect
- DOSAGE IN RENAL FAILURE AND RENAL REPLACEMENT THERAPY: Dose as in normal renal function
- DOSAGE IN PAEDIATRICS: IV:
- For post-operative respiratory depression or over-sedation, give 0.002mg/kg/dose (i.e. dilute 0.4mg to 20ml and then give 0.1ml/kg/dose). Repeat every 2 minutes x 4 if required, then commence infusion by adding 0.3mg/kg to 30ml 5% dextrose and running at 0-1ml/hr (0.01mg/kg/hr).
- For opiate overdose, give 0.01mg/kg (max 0.4mg) (i.e. dilute 0.4mg to 10ml and give 0.25ml/kg/dose). Repeat every 2 minutes x4 if required, then commence infusion by adding 0.3mg/kg to 30ml 5% dextrose and running at 0-1ml/hr (0.01mg/kg/hr)
Category Archives: Anesthesia
ACETAZOLAMIDE (Diamox)
INDICATIONS: 1. Diuretic (particularly in the presence of metabolic alkalosis) 2. Correction of severe metabolic alkalosis
DOSAGE: For diuresis, the dose is usually 250-375 mg stat. If, after an initial response, the patient fails to continue to diurese, do not increase the dose but allow for kidney recovery by skipping medication for a day. Acetazolamide yields best diuretic results when given on alternate days, or for 2 days alternating with a day of rest.Increasing the dose does not increase the diuresis and may increase the incidence of drowsiness and/or paraesthesia. Increasing the dose often results in a decrease in diuresis.
Evidence to support use in patients below the age of 12 years have not been established.
Acetazolamide is contraindicated in the presence of metabolic acidosis. This drug is not indicated in patients on renal replacement therapy.
Acetazolamide is an enzyme inhibitor that acts on carbonic anhydrase, the enzyme that catalyzes the reversible reaction involving the hydration of carbon dioxide and the dehydration of carbonic acid.
CONTRAINDICATIONS 1. Hypersensitivity to acetazolamide or other sulphonamides 2. Metabolic acidosis 3. Cirrhosis (risk of development of hepatic encephalopathy)
Acetazolamide and sodium bicarbonate used concurrently increases the risk of renal calculus formation.
METABOLIC SIDE EFFECTS
Metabolic acidosis, electrolyte imbalance, including hypokalaemia, hyponatraemia, loss of appetite, taste alteration, hyper/hypoglycaemia.
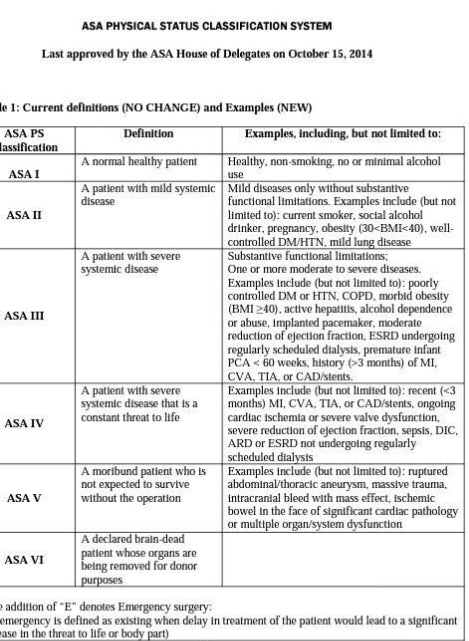
ASA-PS UPDATE 2014
DO YOU KNOW?
A social drinker is ASA II
A smoker is ASA II
Pregnant patient is ASA II
Obese patient is ASA II
Morbid obesity is not ASA II, but ASA III
Alcohol dependence without any documented systemic illness is also ASA III
Premature infant is ASA III
ESRD with regular HD is ASA III
ESRD without regular HD is ASA IV
Evidence of Sepsis or DIC- ASA IV
Intracranial bleed with mass effect is ASA V
A cardiac patient with bowel ischemia is ASA V
Magnesium Sulphate therapy in preeclampsia
Continuous Intravenous Infusion
Magnesium sulfate 4-g to 6-g loading dose diluted in 100 mL fluid administered intravenously over 15 minutes, followed by continuous intravenous infusion at 1 to 2 g per hour. Discontinue 24 hours after delivery or last seizure.
If convulsions persist after 15 min, give up to 2 gram more intravenously as a 20% solution at a rate not to exceed 1g/min. If the patient weighs >70 kg then an additional 2 grams may be given slowly
Only give the next IM dose, or only continue the IV infusion if:
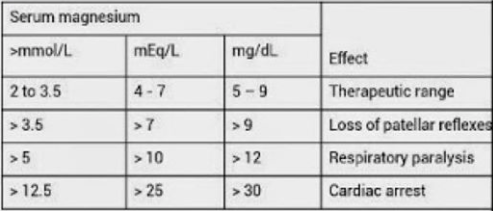
Respiratory rate > 16/min
Urine output > 25 ml/h
Patellar reflexes are present
If urine output < 100 ml in 4 h and there are no other signs of magnesium toxicity, reduce the IV infusion to 0.5 g/h.
If patellar reflexes are depressed and respiration is normal, withhold further doses of magnesium sulfate until the reflexes return and request magnesium level.
If there is concern about respiratory depression , stop magnesium, give oxygen by mask and give:
Calcium gluconate (10mL of 10% solution over 10 minutes)
ACOG TASK FORCE 2013
… For women with severe preeclampsia, the administration of intrapartum and postpartum magnesium sulfate to prevent eclampsia is recommended. For women with preeclampsia undergoing cesarean delivery, the continued intraoperative administration of parenteral magnesium sulfate to prevent eclampsia is recommended.
SPONDYLOEPIPHYSEAL DYSPLASIA
ANESTHETIC CONCERNS
1. Short trachea with 15 rings or less; high chance of accidental one lung ventilation
2. Chances of Laryngeal Stenosis… Some times an unanticipated difficulty for passing tube, may trigger edema and stridor
3. Atlanto axial instability, can cause, massive cord edema, even with moderate neck flexion. Take LATERAL CERVICAL SPINE VIEWS IN FLEXION AND EXTENSION PREOPERATIVELY. If atlantoaxial instability is present and patient requires GA, give MANUAL IN LINE STABILIZATION/ do AWAKE FOB.
4. Restricted lung function accompanied by impending respiratory failure, is a situation, where we may be more inclined towards SAB in such patients (e.g. Pregnancy, where the uterus further compromise lung function). So regional anesthesia may be appropriate, if technically feasible.
5. Technical difficulties with SAB/EDB; epidural space located 2.5 cm from skin was reported in one case.
MULTIPLE SCLEROSIS- ANESTHESIA IMPLICATIONS, TREATMENT
This is the most frequently occurring demyelinating neuromuscular disorder. It’s a chronic progressive disease characterized by repeated exacerbations and partial remissions. It is characterized by the formation of plaques within the brain and spinal cord. These plaques cause demyelination around the axons, resulting in weakness and spasticity as well as sensory dysfunction.Upper motor neurone lesions, cerebellar lesions and sensory deficits are common.
Anaesthetic considerations.
- General anaesthesia does not exacerbate MS. Non-depolarizing neuromuscular blocking agents may be used in normal doses. Caution should be exercised when using depolarizing neuromuscular blocking agents if the patient is debilitated. With the use of Suxamethonium, there is a risk of hyperkalemia
Regional blockade.
- Local anaesthetics may exacerbate the symptoms due to the increased sensitivity of demyelinated axons to local anaesthetic toxicity. New lesions may develop coincidentally at the time of regional blockade and subsequent symptoms may be difficult to differentiate from nerve injury or may be blamed on the block. Complications have been reported with spinal anesthesia (Weak myelin sheath and direct neurotoxicity from LAs have been suggested as reason for this). Epidural may be relatively safer in this regard. (In epidural technique, there will be a lower concentration of LA in white matter). Therefore in general, regional blockade may be relatively contraindicated.
Temperature maintenance is important as symptoms can deteriorate with an increase in temperature, as demyelinated axons are also more sensitive to heat.
Most often, postop exacerbation, if it occurs, is due to fever and infections
We should explain the chance of exacerbation of symptoms before any form of regional anesthesia
TREATMENT
-
The treatment of MS includes treating acute attacks to limit sequelae, prophylactic medications to reduce rate of progression, and symptomatic/supportive therapy
-
Acute attacks are treated with high-dose corticosteroids, i.v. methylprednisolone 500–1000 mg every day divided every 6 or 12 hours; tapered over 7–10 days.
-
Prophylactic medications include the disease-modifying drugs interferon β and glatiramer acetate. Side effects include local infections, fatigue, depression, and anxiety. Regular CBC, LFT, and electrolyte checks are needed.
-
For progressive disease, immunomodulatory drugs such as methotrexate, cyclosporine, cyclophosphamide, azathioprine, total lymphoid irradiation, mitoxantrone (risk of cardiotoxicity), mycophenolate mofetil, or interferon-β may be employed
-
Symptomatic therapies include antidepressants for depression, anticholinergics for hyperreflexic bladder, alpha-blockers or cholinergics/catherization for flaccid bladder, amantadine for fatigue, antispasticity drugs (baclofen, tinzanidine, dantrolene, benzodiazepines) for muscle spasticity, AEDs for tremor, clonus, and pain, and sildenafil for sexual dysfunction. More invasive methods, for example, botulinum toxin injections for focal spasticity or bladder augmentation for spastic bladder may be required in more severe cases
-
Supportive care includes physical/occupational therapy, coping strategies or lifestyle modifications, cognitive-behavioral therapy, and emotional support.
-
In more severe cases, ambulatory aids or wheelchairs and other home-assist devices and caregiver support may be necessary
G6PD Deficiency
# Makes the RBC membrane friable and leads to episodic hemolytic anemia n jaundice
# Stress (surgery or anesthesia), drugs, newborn period, infection, exposure to fava beans are stimulants/risk factors.
# Culprit drug list is long: vit C n K, Methylene blue (caution in rx of methemoglobinemia),SNP, prilocaine.…
# Check for anemia, need for transfusion, jaundice(can also appear postop),cataract(increased incidence)
# Malignant Hyperthermia has been reported in association
# Avoid elective surgeries during a hemolytic episode
# Give a folic acid suppliment perioperatively
# Paracetamol,Phenytoin,L Dopa etc are safe.
SJOGRENS SYNDROME-anesthesia implications
 🏳️🌈Preoperative abnormalities
1. Symptoms of the sicca syndrome include dryness of the eyes and skin.
2. Check for associated RA, SLE, scleroderma, the polymyositis, polyarteritis nodosa, chronic active hepatitis, and Grave’s disease.
3.Lung / airway : desiccation of the nose and bronchial tree, obstructive airways disease, interstitial lung disease
4.sensory / motor neuropathy may occur and CNS lesions have been described.
5.The patient may be taking corticosteroids or occasionally immunosuppressive agents.
🏳️🌈Anaesthetist’s concerns
1. Sometimes gross swelling of the salivary glands may make mask anaesthesia difficult.
2.The problems of pulmonary disease, if present.
3.The dry eyes are susceptible to damage during anaesthesia.
4.Allergy to antimicrobial agents, particularly penicillin, cephalosporins and trimethoprim
Management
1. careful assessment of the primary disease, and of any pulmonary involvement.
2. Drying agents should be avoided if possible.
3. The eyes should be protected with pads.
4. Anaesthetic gases should be humidified.
5. Steroid supplements may be required.
6. Care should be taken when prescribing antimicrobial agents
Practical issues in blood transfusion in pediatrics
1. Amount of transfusion to be given: It has been seen that transfusion with PRBC at a dose of 20 mL/kg is well tolerated and results in an overall decrease in number of transfusions compared to transfusions done at 10 mL/kg. There is also a higher rise in hemoglobin with a higher dose of PRBCs.
2. Properties of RBC products used in neonatal transfusion: a. RBCs should be freshly prepared and should not be more than 7 days old. This translates into a high 2, 3-DPG concentration and higher tissue extraction of oxygen.
3.Blood should be of newborn’s ABO and Rh group. It should be compatible with any ABO or atypical red cell antibody present in the maternal serum.
4. Volume and rate of transfusion:
a. Volume of packed RBC = Blood volume (mL/kg) x (desired minus actual hematocrit)/ hematocrit of transfused RBC
b. Rate of infusion should be less than 10 mL/kg/hour in the absence of cardiac failure.
c. Rate should not be more than 2 mL/kg/hour in the presence of cardiac failure.
d. If more volume is to be transfused, it should be done in smaller aliquots.
ANESTHESIA IMPLICATIONS-HAEMOCHROMATOSIS
/MNEMO/: ‘HEME LDH’
1. Liver Dysfunction
2. Diabetes
3. Heart Failure

